What I treat · Erectile dysfunction
Erectile dysfunction, treated as a finding rather than a nuisance
An erection depends on arteries, nerves, hormones and mood all working at once. “Try a tablet” is a reasonable first move and a poor substitute for knowing which of those four has given way.
In a man over forty, new erectile difficulty is a vascular observation as much as a sexual one. The arteries supplying the penis are considerably narrower than the coronary arteries and narrow sooner, which is why erectile dysfunction often appears some years before any cardiac symptom — a well-established association, and the reason assessment here includes blood pressure, glucose, lipids and testosterone rather than a prescription alone. For some men that conversation turns out to matter more than the erections did.
Treatment is a ladder, and most men are stopped on the first rung. Tablets fail for a substantial minority, frequently because the dose was too low, the drug was taken wrongly, or low testosterone was never corrected — all of which are worth exhausting before concluding that tablets do not work. Above them sit vacuum devices and injection therapy, which succeed in many men for whom tablets have not. Where nothing restores reliable function, an implant does, with the highest satisfaction figures of any treatment in this field.
The assessment
- Cardiovascular and metabolic screen
- Morning testosterone and hormone profile
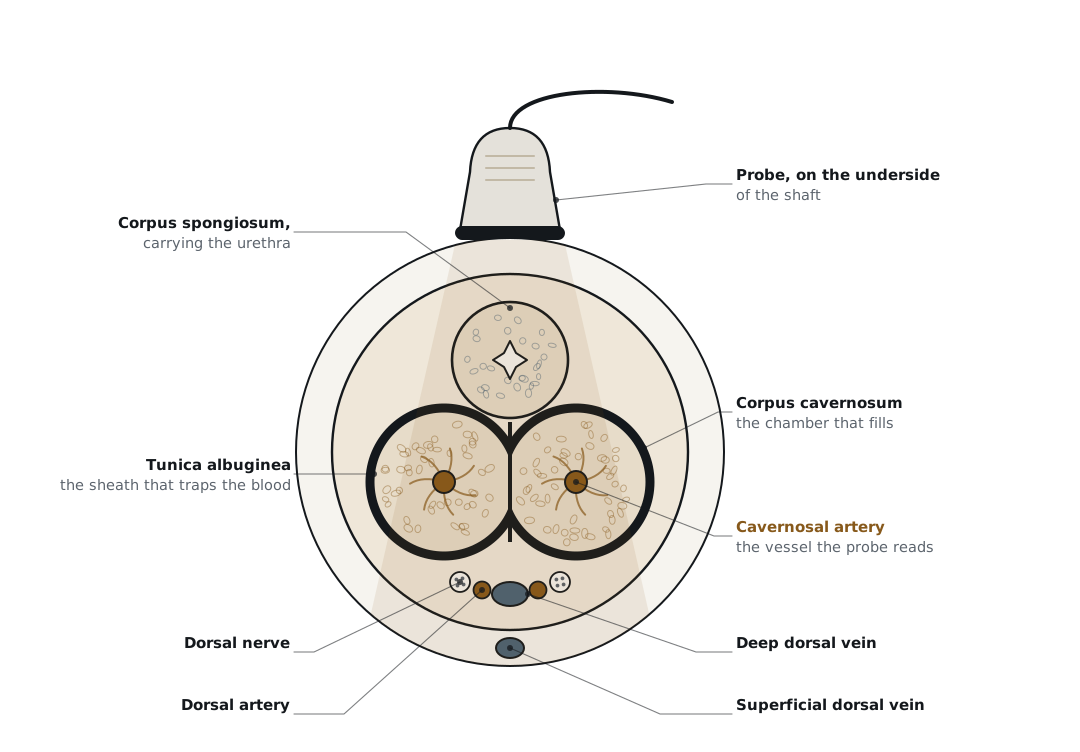
- Penile duplex ultrasound where the cause is unclear
- Review of medication that may be contributing
Treatments offered
- Optimisation of oral therapyBAUS leafletA24/079
- Testosterone replacement where indicated
- Intracavernosal injection therapy
- Vacuum erection devicesBAUS leafletA24/091
- Inflatable and malleable penile prosthesisBAUS leafletA24/082
The leaflets above are published by the British Association of Urological Surgeons (BAUS) and open in a new tab. They are linked, not hosted or altered.
Oxford Men’s Health
Written and reviewed by Mr Musaab Yassin, Consultant Urological Surgeon & Andrologist. FRCS (Urol) · GMC 6118378 ·