Mr Musaab YassinOxford Men’s Health
← Oxford Men’s Health

What I treat · Erectile dysfunction

Erectile dysfunction, treated as a finding rather than a nuisance

An erection depends on arteries, nerves, hormones and mood all working at once. “Try a tablet” is a reasonable first move and a poor substitute for knowing which of those four has given way.

In a man over forty, new erectile difficulty is a vascular observation as much as a sexual one. The arteries supplying the penis are considerably narrower than the coronary arteries and narrow sooner, which is why erectile dysfunction often appears some years before any cardiac symptom — a well-established association, and the reason assessment here includes blood pressure, glucose, lipids and testosterone rather than a prescription alone. For some men that conversation turns out to matter more than the erections did.

Treatment is a ladder, and most men are stopped on the first rung. Tablets fail for a substantial minority, frequently because the dose was too low, the drug was taken wrongly, or low testosterone was never corrected — all of which are worth exhausting before concluding that tablets do not work. Above them sit vacuum devices and injection therapy, which succeed in many men for whom tablets have not. Where nothing restores reliable function, an implant does, with the highest satisfaction figures of any treatment in this field.

The honest trade-off The ladder runs in one direction only. Tablets, vacuum devices and injections are all reversible — stop them and nothing has been lost. An implant produces the most dependable erection available and the highest satisfaction of any treatment for this problem, and it permanently replaces the natural erectile tissue, so nothing further can be tried afterwards. That is why it is the last rung rather than the first, and why the discussion takes a full appointment.
Worth knowing before you pay for it Low-intensity shockwave therapy is advertised heavily and directly to patients. The trials behind it are mostly small and short, the benefit where it exists is modest, and European guidance gives it only a weak recommendation, in mild vascular cases. It may be reasonable for some men. It is not the breakthrough the advertising describes, and a course of it is not cheap.
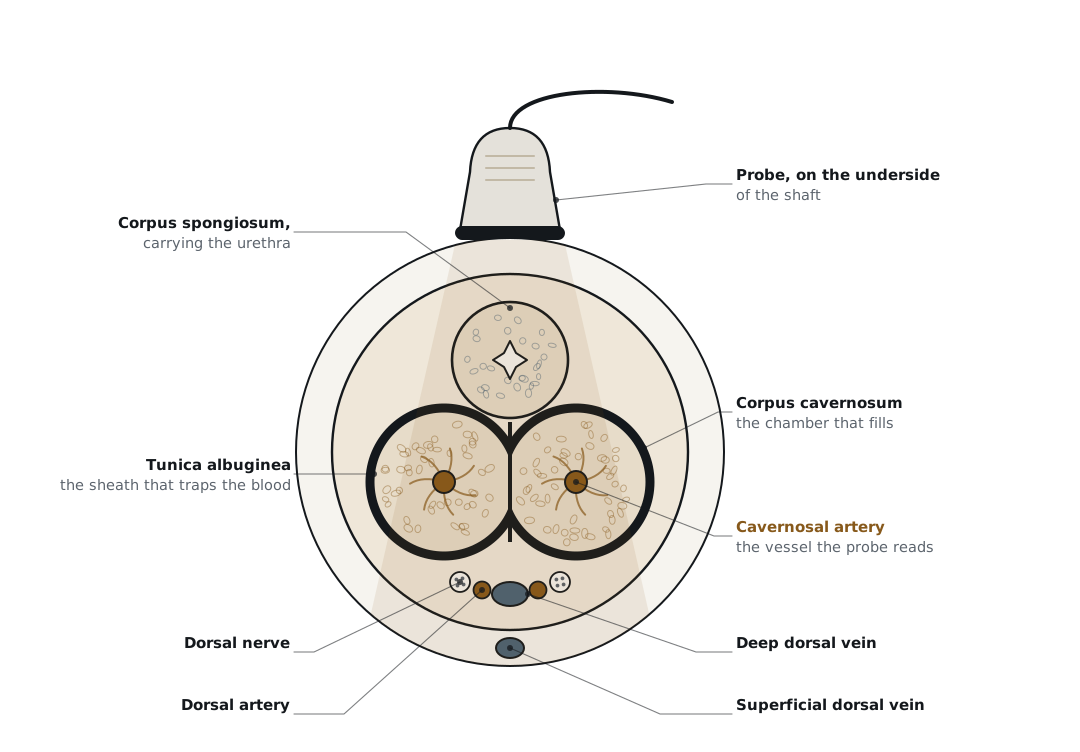
Cross-section of the penile shaft: the two corpora cavernosa with their cavernosal arteries, the corpus spongiosum carrying the urethra, the dorsal vessels and nerves, and a Doppler probe applied to the ventral surface.
Where the probe goes, and the artery it reads.

Oxford Men’s Health

Written and reviewed by Mr Musaab Yassin, Consultant Urological Surgeon & Andrologist. FRCS (Urol) · GMC 6118378 ·

Evidence Notes · Erectile dysfunction

Read the case against a treatment, before you agree to it.

Erectile dysfunction has no note of its own yet: the treatments are established and the evidence is set out in the penile implant guide. What is here is the reading that bears on erectile function itself; the caution about low-intensity shockwave therapy is in the overview above. The vacuum device note is written around curvature and length, so it belongs with Peyronie’s disease rather than here.

Relevant to erectile dysfunction

StrongRandomised trials and systematic reviews agree.
ReassuringConsistent, but resting partly on observational work.
ModerateReal, from smaller or less rigorous studies.
LimitedToo little evidence to rely on. Said plainly.
The full collection, all twelve → How to read a trial result

Common Questions · Erectile dysfunction

The ten questions men ask before they book.

Short, referenced answers to the questions that come before a diagnosis exists — written to be read at eleven at night, by someone who has not told anyone yet. Each is referenced to guidelines, systematic reviews and trials, with the studies listed at the foot of its page.

All fifty-five, across every condition, are on the practice page.

Before your visit

Fifteen minutes now saves twenty in the room.

Complete the questionnaire before you come. Nothing is saved or transmitted — you print the summary or copy it into an email, and it stays entirely in your control.

05 · Men’s sexual health

Erections, testosterone and desire

Erectile dysfunction, premature ejaculation, low testosterone, and the changes that follow prostate treatment. A dedicated questionnaire for this area is in preparation.

Get in touch →
What to bring Three things

Any previous scans or reports, a list of your current medication, and the completed questionnaire if you have had time.

How long Allow up to an hour

The consultation itself takes at least twenty minutes. Allow up to an hour if you are having a flow test, a scan, bloods or a urine test on the day.

Coming with someone Welcome

Partners are welcome throughout, and for fertility discussions it is often better if you both come.

The other areas

Each area has a page of its own.

Booking, fees and the four ways to get in touch are on the practice page.

Call the practice Send an enquiry